

Nobody had reviewed his diet. Nobody had measured his albumin or prealbumin. Nobody had checked his zinc or vitamin C. Everyone was locked in on the dressings, the offloading, the size measurements — the construction site itself. Meanwhile his body was short the raw materials it needed to actually close the thing it was being asked to close.
Wound healing nutrition might be the single most evidence-dense and most clinically ignored corner of medicine. Sophisticated technology everywhere you look — negative pressure wound therapy, bioengineered dressings, growth factor treatments, hyperbaric oxygen — deployed routinely, while the nutritional status that determines whether any of it actually works gets a shrug. A wound is a construction project. Dressings and devices manage the site.
Nutrition delivers the building materials. Best project manager in the world doesn’t matter if the lumber truck never shows.
This piece walks the nutrition of wound healing systematically — the macro- and micronutrients driving each phase of the healing cascade, the evidence behind specific supplements, what malnutrition and targeted deficiencies do to outcomes, and the practical tools clinicians and patients actually have for fixing nutritional status.
Surgical incision, diabetic foot ulcer, pressure injury, traumatic wound, burn — doesn’t matter which. The nutritional principles hold across all of them. And the evidence for getting them right is, frankly, compelling.
The Wound Healing Cascade: What Nutrition Has to Supply
Wound healing runs through four sequential, overlapping phases: hemostasis, inflammation, proliferation, remodeling. Each phase demands different nutrients, and a deficiency at any one phase drags down everything downstream. Understand what each phase needs and you understand both the consequences of specific deficiencies and when to intervene.
Hemostasis happens within minutes: platelets aggregate, the coagulation cascade seals things up. Driven mostly by platelet function — adequate omega-3:omega-6 balance, vitamin K for coagulation factor synthesis, calcium — and vascular response. Nutritional deficiency rarely limits acute hemostasis, unless the patient’s on warfarin (which antagonizes vitamin K) or has severe protein-energy malnutrition.
The inflammatory phase (days 1–4) is immune cell recruitment — neutrophils first, then macrophages — clearing debris, killing bacteria, secreting the growth factors that kick off the next phase. Protein-dependent, all of it: neutrophil and macrophage synthesis, antibody production, complement activity, cytokine signaling. All amino-acid hungry.
Arginine matters especially here — substrate for nitric oxide production by immune cells, which handles antimicrobial and vasodilatory duty essential for perfusion and bacterial clearance at the wound site. Glutamine fuels the rapidly dividing immune cells and becomes conditionally essential under physiological stress.
The proliferative phase (days 4–21) is the hungriest of all: fibroblasts migrate in and start synthesizing collagen for the granulation matrix; endothelial cells proliferate for new blood vessels; epithelial cells migrate across the surface to close it up.
Collagen synthesis needs vitamin C (cofactor for the prolyl and lysyl hydroxylase enzymes that crosslink collagen chains), zinc (cofactor for the metalloenzymes governing collagen maturation and cell division), and adequate protein — proline, glycine, hydroxyproline are collagen’s core amino acids. Angiogenesis needs iron (for hemoglobin to perfuse the new vessels), copper (for ceruloplasmin and lysyl oxidase), and vitamin A (regulating the VEGF pathways that drive vessel growth).
Remodeling (week three through month two) is the slow swap of type III collagen — the “quick” scaffolding kind — for the stronger type I, plus organizing the fibers along stress lines. Needs sustained protein, plus ongoing zinc and copper for the metalloenzymes regulating collagen turnover. Skip these and you get weak, brittle scar tissue that reopens at the first excuse.
Protein: The Single Most Critical Macronutrient for Wound Healing
Of every nutritional requirement in wound healing, protein deficiency does the most damage, most consistently. It hits every phase: weaker neutrophil and macrophage function, impaired fibroblast proliferation, reduced collagen synthesis, slower epithelialization, weaker tensile strength in the finished wound.
Casey and colleagues, writing in the Journal of Wound, Ostomy and Continence Nursing, found serum albumin below 3.5 g/dL — a protein-status marker — was the single strongest predictor of healing complications and non-healing in 120 patients with chronic wounds. Stronger than wound type. Stronger than wound size. Stronger than comorbidities.
Protein needs during healing blow past normal maintenance numbers. RDA for a healthy adult: 0.8 g/kg/day. For patients with wounds, most evidence-based guidelines land at 1.2–2.0 g/kg/day depending on severity. For a moderate wound — stage 3 pressure injury, say, or a surgical wound healing by secondary intention — those guidelines sit at the 1.25–1.5 g/kg/day end of that range.
A patient with severe burns (over 40% body surface area) or multiple traumatic wounds may need 2.0–2.5 g/kg/day or more — the catabolic demand of that much tissue destruction and immune activation is extraordinary.
Standard hospital meals consistently miss these targets. One study of hospitalized patients with pressure injuries found 72% consuming below their calculated protein requirement, and 48% under 75% of it. The gap widens further in elderly patients, where anorexia, dysphagia, dental problems, and reduced appetite stack on top of already-elevated needs.
Supplementation — high-protein oral nutritional supplements, nasogastric feeding, or parenteral nutrition when enteral isn’t feasible — isn’t a luxury add-on here. It’s a treatment.
Source matters less than quantity and amino acid completeness. Complete proteins — animal sources, soy, well-planned plant combinations — deliver the branched-chain amino acids (leucine, isoleucine, valine) that drive muscle protein synthesis plus the conditionally essential ones (arginine, glutamine) that become essential under catabolic stress. Whey protein isolate is a practical supplemental pick, given its leucine content, fast digestibility, and high biological value.
Arginine: The Conditionally Essential Amino Acid of Wound Healing
Arginine occupies odd territory — both a structural protein precursor and a metabolic precursor to critical bioactive molecules. Normally non-essential; the body makes enough on its own. But during wound healing, surgery, burns, or any major physiological stress, demand outpaces synthesis. Conditionally essential.
It’s the substrate for nitric oxide synthase in macrophages and endothelial cells, producing nitric oxide with direct antimicrobial activity against wound pathogens, promoting angiogenesis via VEGF activation, and mediating the vasodilation that keeps blood flowing to the healing bed. It also converts to proline — a major collagen amino acid — via the ornithine-proline pathway in fibroblasts, feeding structural substrate straight into collagen deposition.
Multiple RCTs back arginine supplementation as an accelerant. A landmark Barbul et al. study in the Journal of Parenteral and Enteral Nutrition found arginine supplementation (24.8 g/day for two weeks) in postoperative patients significantly increased wound hydroxyproline content — a collagen marker — and improved breaking strength at suture removal versus placebo.
A systematic review by Stechmiller et al. found arginine-enriched oral supplements (commonly delivered as Juven or Arginaid) consistently improved healing outcomes in pressure injury patients over standard nutrition.
On dosing: the studies showing benefit typically used 15–30 g/day of supplemental arginine, well beyond what standard diets deliver (typical intake sits around 4–5 g/day). Commercial wound-healing formulas — Juven, ProSure, Resource Arginaid — deliver therapeutic arginine alongside other wound-relevant nutrients, a practical delivery format.
Straight arginine in capsule or powder form is also available, but if using isolated arginine, make sure the cofactors — vitamin C, zinc, copper — are adequate too, given how interdependent they are in the collagen synthesis pathway.
Vitamin C: The Collagen Synthesis Gatekeeper
Severe deficiency — scurvy — is practically the textbook picture of wound healing failure: poor healing, perifollicular hemorrhages, bleeding gums, previously healed wounds reopening.
You don’t need clinical scurvy to impair healing. Subclinical deficiency (serum ascorbate below 11 μmol/L) tracks with impaired healing, higher infection rates, and reduced collagen production across multiple studies. A 2019 cross-sectional study found vitamin C deficiency in 21% of hospitalized patients with non-healing wounds — versus roughly 7–10% in the general population.
Hospitalization itself burns through vitamin C — stress hormones, inflammation, tissue repair all consume ascorbate fast, and hospital food rarely delivers enough to keep pace.
Vitamin C also serves as a potent antioxidant at the wound site, protecting newly made collagen and dividing cells from the reactive oxygen species that activated neutrophils and macrophages throw off. It reduces oxidative inactivation of the collagen-degrading metalloproteinases — which need tight regulation, since too much MMP activity destroys the matrix and too little blocks remodeling — and protects proliferating fibroblasts from oxidative-stress apoptosis.
Dosing: RDA (75–90 mg/day) covers maintenance but is likely insufficient during active healing under real tissue demand. Most wound care guidelines recommend 500–1000 mg/day during active healing in at-risk patients. Higher doses (1–2 g/day) for severe or chronic wounds, burns, or documented deficiency.
It’s water-soluble, rapidly excreted — doses above 1 g/day are largely wasted, urinary excretion spikes above 500 mg per dose — so divided dosing (500 mg twice daily) beats one large dose for maintaining tissue saturation.
Zinc: Metalloenzyme Master of Wound Repair
Zinc’s a cofactor for over three hundred human enzymes, and a lopsided share of them run wound healing: zinc-dependent metalloproteinases regulate matrix remodeling; zinc-containing superoxide dismutase guards healing tissue against oxidative damage; zinc-dependent alkaline phosphatase handles tissue mineralization; and thymidine kinase and DNA polymerase — the enzymes driving DNA replication in fibroblasts, keratinocytes, and immune cells alike — need zinc to function at all.
The clinical evidence spans five decades. A landmark 1967 RCT by Pories et al. in the Lancet found zinc sulfate supplementation significantly sped leg ulcer healing versus placebo — one of the earliest RCTs in this whole field.
Meta-analyses of zinc supplementation in leg ulcers and pressure injuries consistently find benefit in zinc-deficient patients, more modest effects in zinc-sufficient ones. Correcting deficiency, unsurprisingly, produces the biggest gains.
Deficiency’s common in wound care populations — roughly 30–40% of elderly patients in wound care settings show biochemical zinc deficiency, with patients who have GI disease (Crohn’s, celiac, post-bariatric surgery), chronic kidney disease, or long-term diuretic use at particular risk.
Standard serum zinc testing is imprecise — a poor proxy for total body zinc, homeostatically maintained at the expense of tissue stores — but values below 70 μg/dL are clinically significant and warrant supplementation regardless of the test’s limitations.
Protocol: zinc sulfate 220 mg three times daily (roughly 150 mg elemental) was the dose in early trials, and it worked. More recent practice leans toward 40–80 mg elemental daily, less likely to cause nausea or the copper depletion that comes with high-dose zinc (zinc and copper compete for intestinal absorption; chronic high-dose zinc can induce copper deficiency).
Copper depletion is the reason zinc courses above 40 mg elemental running longer than four to eight weeks are normally paired with supplemental copper.
Vitamin A: The Forgotten Wound Healer
Vitamin A works wound healing through three separate mechanisms: regulating keratinocyte differentiation and proliferation via RAR nuclear receptors, stimulating fibronectin production (an extracellular matrix scaffold protein), and supporting the macrophage and T-cell function driving the inflammatory phase. Deficiency means impaired epithelialization, reduced collagen synthesis, higher infection susceptibility, and weaker immune response at the wound.
Particularly relevant in two contexts: patients on long-term systemic corticosteroids, and patients post-bariatric surgery or with fat malabsorption syndromes. Corticosteroids directly impair healing by suppressing the inflammatory phase and cutting collagen synthesis — effects substantially reversed by vitamin A.
A classic Hunt et al. study found topical vitamin A applied to steroid-treated wounds normalized macrophage function and collagen synthesis — suggesting a direct antagonism between glucocorticoid and retinoid signaling in healing tissue. Oral vitamin A at 10,000–25,000 IU/day for corticosteroid-treated wounds is documented across multiple series, though prolonged use at this dose needs toxicity monitoring.
Fat malabsorption syndromes — bariatric surgery, Crohn’s, primary biliary cholangitis, exocrine pancreatic insufficiency — impair absorption of all fat-soluble vitamins, vitamin A included. Non-healing wounds in post-bariatric patients should trigger comprehensive micronutrient assessment, vitamin A levels among them. Fat-soluble vitamin deficiency after Roux-en-Y gastric bypass is far more common than usually recognized, and post-bariatric wound healing problems are partly nutritional, not purely vascular or infectious.
Omega-3 Fatty Acids and the Inflammatory Phase

Omega-3s modulate rather than suppress inflammation — shifting the balance away from pro-inflammatory prostaglandin E2 (from arachidonic acid/omega-6) and toward less inflammatory eicosanoids and the specialized pro-resolving mediators (resolvins, protectins, maresins) that actively resolve inflammation without shutting it down prematurely.
In chronic non-healing wounds — where the pathology is typically an inflammatory phase stuck in place, excessive MMP activity chewing up the matrix as fast as it’s laid — omega-3s’ pro-resolving properties are directly relevant therapeutically.
A 2012 McDaniel et al. study in Wound Repair and Regeneration found omega-3 supplementation (3 g/day EPA+DHA) significantly cut inflammatory markers in chronic wound exudate and improved closure time in venous leg ulcer patients versus placebo.
Timing matters: in acute wounds during the first two to three days, the inflammatory phase is beneficial and necessary — excess anti-inflammatory intervention here could theoretically get in the way. In chronic wounds stuck in inflammation for weeks, pro-resolving support is indicated.
In practice that puts omega-3 intake of 1–2 g/day EPA+DHA, from food or supplements, into the picture for wound care patients generally, with the higher 3–4 g/day range appearing in chronic inflammatory wounds, adjusted for anticoagulant use — omega-3 above 3 g/day carries mild antiplatelet activity.
Glutamine: The Immune Fuel and Gut Barrier Protector
Glutamine’s the most abundant amino acid in the body and the primary fuel for rapidly dividing cells — the lymphocytes, macrophages, and neutrophils central to the inflammatory phase, plus the intestinal enterocytes maintaining gut barrier integrity. Under significant physiological stress — surgery, severe burns, major trauma — it’s consumed faster than the body can make it, depleting plasma and intracellular stores and hurting both immune function and gut barrier integrity.
A Wischmeyer et al. meta-analysis of glutamine supplementation in surgical and critically ill patients found significantly lower wound infection rates, shorter hospital stays, and better overall outcomes versus controls. Benefit was most pronounced with burns, major abdominal surgery, and critical illness.
Several European and North American clinical nutrition guidelines (ESPEN, ASPEN) recommend glutamine supplementation for severely injured and burn patients, though routine use across all wound care patients has less definitive support.
The gut barrier connection matters because major wounds create conditions — reduced enteral intake, antibiotic use, physiological stress — that favor dysbiosis and barrier disruption. Bacterial translocation from a compromised barrier adds to the systemic inflammatory burden that slows healing. Glutamine supports enterocyte integrity and gut barrier function, potentially cutting that systemic burden.
At 20–30 g/day for hospitalized wound patients under significant physiological stress, glutamine supplementation is mechanistically justified and backed by outcome data in higher-acuity contexts.
Nutritional Assessment Tools for Wound Care Settings
Identifying nutritional risk requires validated tools beyond simple serum albumin — clinically useful, sure, but albumin reflects inflammatory status as much as nutritional status. It’s a negative acute-phase reactant; it drops with inflammation regardless of intake. Several validated screening instruments fill the gap.
The Mini Nutritional Assessment (MNA), validated specifically in older adults, identifies malnutrition and malnutrition risk through twelve questions covering food intake, weight loss, mobility, neuropsychological status, and anthropometric measures. Its sensitivity in long-term care settings — where pressure injury patients commonly live — is well-established. The Malnutrition Universal Screening Tool (MUST) is a five-step screen applicable across settings, using BMI, unintentional weight loss, and acute illness to classify risk.
Biochemically, serum prealbumin (transthyretin, half-life 2–3 days) responds faster to nutritional status change than albumin (half-life 14–21 days), dropping with acute protein-energy malnutrition and recovering faster with improvement. Prealbumin below 15 mg/dL flags significant protein malnutrition absent acute inflammation (which can also lower prealbumin regardless of nutrition).
CRP measured alongside prealbumin contextualizes the result: low prealbumin with low CRP suggests genuine depletion; low prealbumin with high CRP may just be inflammation-driven suppression.
The Wound Healing Index (WHI), developed by Grey and Harding, folds nutritional status assessment into its core components — reflecting the clinical consensus that nutrition can’t be separated from comprehensive wound assessment. Every patient with a non-healing or complex wound deserves nutritional assessment. Not a dietary history question tacked onto a chart. A validated tool, applied by someone with nutritional expertise, followed by quantitative intake analysis and targeted supplementation.
Diabetes and Wound Healing Nutrition: Special Considerations
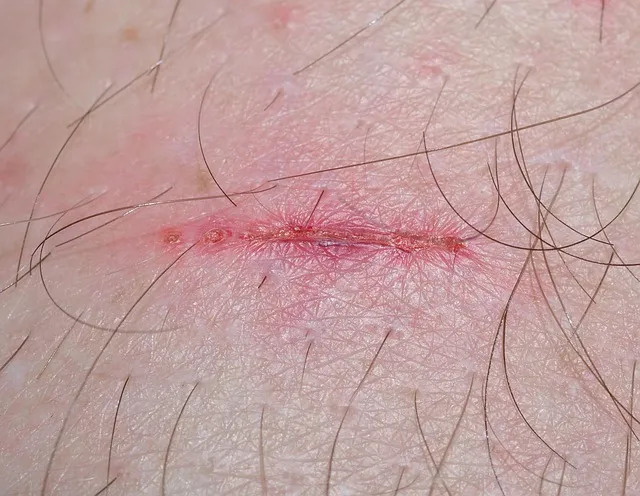
For DFU patients, the nutritional framework’s the same as elsewhere, plus glycemic control objectives. Higher protein (1.5–2.0 g/kg/day) fits the elevated catabolic state, but source matters — whey specifically stimulates insulin secretion, potentially helpful for postprandial glucose management in type 2 diabetics, while very high protein intake in diabetic nephropathy may need renal monitoring.
Omega-3s at therapeutic doses (2–4 g/day) are particularly useful for DFU, where the chronic inflammatory stuck phase runs even deeper than in non-diabetic wounds. Zinc supplementation has specific DFU data behind it: a 2013 study found zinc significantly improved healing rates in DFU patients with documented deficiency.
Vitamin D matters specifically in diabetic wound care because hypovitaminosis D independently impairs insulin sensitivity, immune function, and antimicrobial peptide (defensin) production in the wound environment. A 2018 RCT found vitamin D supplementation improved DFU healing outcomes specifically in vitamin D-deficient patients.
Given that vitamin D deficiency runs extremely high in the diabetic population — 60–70% of type 2 diabetics in northern latitudes show 25-OH-D below 30 ng/mL — routine supplementation to reach adequate levels is important, and overlooked far too often, in DFU management.
Reader Questions About Wound Healing Cascade
How much protein do I actually need after surgery to heal properly?
Most adult surgical patients need 1.2–2.0 g/kg/day during healing — substantially above the standard 0.8 g/kg/day recommendation. For a 70 kg adult with a moderate surgical wound, that’s 84–140 grams of protein daily. A typical hospital diet delivers 60–70 grams. Most surgical patients are running a protein deficit and nobody’s told them.
Actively supplementing protein — eggs, Greek yogurt, lean meats, legumes, or supplements like whey powder and commercial high-protein drinks — is appropriate for the four-to-six-week early healing window. One of the most modifiable factors in wound outcomes, and most patients have no idea their protein intake is a medical variable.
Is there anything I should avoid eating while a wound heals?
Excess alcohol tops the evidence-based avoidance list — it impairs immune function, depletes zinc and B vitamins, and raises infection and delayed-healing risk. Ultra-processed foods are a secondary concern: they crowd out nutrient-dense foods without contributing much, and their omega-6-heavy fat profile relative to omega-3 feeds the pro-inflammatory prostaglandin pathways that can chronify wound inflammation. High-glycemic foods matter specifically for diabetic patients, where glycemic control directly affects healing.
Beyond that, the focus should be adequacy — getting enough of what heals the wound — rather than restriction. Deficit is a far bigger and more common problem in wound care patients than excess.
Should I take a multivitamin while healing from a wound?
A high-quality multivitamin is a reasonable baseline — it efficiently covers multiple potential micronutrient gaps that might otherwise need individual testing. But it’s built for maintenance doses, not wound healing optimization.
A multivitamin won’t supply therapeutic zinc (25–40 mg, versus the typical 8–15 mg), therapeutic vitamin C (500–1000 mg, versus 60–100 mg), or the arginine, glutamine, and omega-3s with specific wound healing evidence. Think of it as a safety net against deficiency, with targeted supplementation layered on top for the nutrients with strong evidence.
How does hydration affect wound healing?
Adequate hydration matters because tissue oxygenation — delivered by a cardiovascular system whose performance depends on adequate circulating blood volume — determines how well the wound bed gets perfused. A dehydrated patient has less circulating volume, less cardiac output, less tissue perfusion; the healing tissue gets less oxygen, fewer nutrients, and slower clearance of inflammatory waste.
Clinically, dehydration also shifts wound exudate production and creates a drier wound environment that impairs cell migration — especially epithelial cells crossing the wound surface during epithelialization. Targeted hydration — enough fluid to maintain pale yellow urine, roughly 30–35 mL/kg/day in adults without fluid restriction — is a non-negotiable piece of healing optimization.
Can nutritional supplements alone heal a chronic wound?
No. Necessary, not sufficient. Chronic wounds that won’t heal usually have several contributing factors at once: inadequate wound care (wrong dressings, unaddressed biofilm), impaired perfusion, infection, mechanical offloading failure, and nutritional deficiency. Fix the nutrition alone and ignore the rest, and you get partial benefit at best.
The right frame: adequate nutrition is a prerequisite — no amount of topical wound management will succeed if the body lacks building materials — but nutritional optimization unlocks the benefit of good wound care rather than replacing it. Both matter. Neither alone is enough.
Burns and Catastrophic Wound Nutrition: The Extreme End of the Spectrum
Major burns are the most extreme nutritional challenge wound care has to offer — and understanding burn nutrition requirements throws the general wound healing principles into their starkest form. A major burn (over 20% body surface area) triggers a metabolic response as severe as anything documented in human physiology: the hypermetabolic response can increase resting energy expenditure 100–200%, blowing past what any normal diet can cover without deliberate, aggressive nutritional support.
Protein requirements in major burns are extraordinary: 2.5–3.5 g/kg/day in severe cases — roughly 175–245 grams daily for a 70 kg patient. Healing demands (collagen synthesis, immune cell production) scale with wound area, and in a major burn that means protein loss equivalent to several times daily synthesis capacity, happening all at once.
Nitrogen balance data from major burn patients consistently shows massive negative balance even under aggressive support; the goal becomes minimizing the deficit rather than achieving actual balance.
Enteral nutrition started within six hours of major burn injury — early enteral nutrition — has been shown across multiple RCTs to reduce gut mucosal atrophy, reduce bacterial translocation, reduce systemic infection risk, and improve survival versus delayed or parenteral feeding. The gut-wound connection is especially dramatic in burns: massive systemic inflammation and splanchnic hypoperfusion rapidly wreck gut barrier integrity, making early enteral feeding both a nutritional strategy and an anti-infection strategy at once.
Modern burn care guidelines universally treat early enteral nutrition as treatment. Not support. Treatment.
Micronutrient supplementation in major burns goes far past what oral supplementation covers in typical wound care. Vitamin C at 60–80 mg/kg/day — roughly 4–5.6 grams for a 70 kg patient — during the first 24–48 hours post-burn has been shown to reduce resuscitation fluid requirements and improve outcomes through antioxidant protection of the endothelium. Zinc, copper, and selenium all deplete through wound exudate in major burns and need replacement well past RDA levels.
Vitamin D deficiency is nearly universal in major burn patients and requires aggressive repletion. The burn unit is wound healing nutrition in its most systematically studied form, and the principles — protein first and high-dose, therapeutic vitamin C and zinc, arginine and glutamine supplementation — apply in scaled-down form across every wound care setting.
Chen Wei’s story ended reasonably. When a wound care specialist reviewed his case at week eight, she ordered a full nutritional workup. Serum prealbumin: 12 mg/dL, significantly low. Zinc: 65 μg/dL. She estimated his actual protein intake at roughly 45 grams/day against a requirement of 100–120 grams.
She prescribed a high-protein oral supplement twice daily, zinc gluconate 30 mg elemental daily, vitamin C 500 mg twice daily, and dietary counseling for his overall intake. Six weeks later the wound was granulating actively, down 40% in size. Eight weeks after that, closed. The dressings, the clinic visits, the diligent offloading — all present for months, going nowhere. What changed was delivery of building materials.
The body, given what it needed, built.
The wound healing nutrition story is ultimately about taking biology seriously. We know collagen requires vitamin C. We know cell division requires zinc. We know immune function requires protein. We know arginine drives the nitric oxide production that perfuses healing tissue. We know all of this. We measure it, study it, publish it.
And then we bring patients into wound care clinics and ignore their diets while changing their dressings. The gap between what we know and what we do isn’t a knowledge problem. It’s a systems problem, a priority problem, an attention problem. Closing it — making nutritional assessment as routine as wound measurement, targeted supplementation as standard as dressing selection — sits entirely within current wound care capability.
It just requires deciding it matters. It does.
Pressure Injury Prevention: Nutrition Before the Wound
Pressure injuries — ulcers developing at bony prominences in immobile patients — are wound healing nutrition in a preventive frame: nutritionally replete patients resist pressure-driven tissue breakdown better than malnourished ones. Malnutrition is one of the strongest independent risk factors for pressure injury in hospitalized and long-term care patients.
Mechanistically: reduced subcutaneous tissue mass (less padding over bony prominences), impaired skin integrity from deficiencies in barrier-maintenance nutrients (vitamin C, zinc, vitamin A), and reduced immune capacity to handle the micro-injuries that accumulate under prolonged pressure.
The Braden Scale — the most widely used pressure injury risk tool — includes a nutrition subscale capturing oral intake adequacy, tube feeding status, and supplement use. A score of 3 or below on that subscale significantly raises overall risk and should trigger automatic dietitian referral.
Folding nutrition into systematic pressure injury risk assessment is best practice — it acknowledges nutrition isn’t background noise but a primary determinant of skin integrity and wound resistance.
Prevention nutrition for high-risk patients mirrors treatment nutrition. Adequate protein (minimum 1.2–1.5 g/kg/day) maintains the subcutaneous tissue cushioning bony prominences. Adequate vitamin C maintains collagen turnover keeping skin structurally sound. Adequate zinc maintains the metalloenzyme function governing skin cell renewal. Adequate hydration maintains turgor and perfusion.
Same nutrients, same doses, same biological purpose — whether preventing the wound or healing it. Prevention is just wound healing before the injury, which is infinitely easier than after.
Practical implementation — hospitals, nursing homes, home care — requires systematic identification of nutritionally at-risk patients before wounds develop, not reactive intervention weeks into a wound that’s failing to heal. Routine screening on admission (MNA, MUST, or equivalent), automatic dietitian referral for at-risk patients, proactive supplementation protocols for high-pressure-injury-risk patients — this is what evidence-based wound prevention practice requires. The evidence is clear.
The implementation, as in so much of evidence-based medicine, remains inconsistently delivered.
References
Editorial StandardsCorrectionsMedical DisclaimerAbout Our ContentAffiliate DisclosureSite Map