

His dentist had fitted him with a night guard, his doctor had prescribed a muscle relaxant, and his therapist had identified a pattern of chronic muscle tension running from shoulders to forehead that had been building since his first law firm job. Held together by tension, in his own words.
His therapist recommended Progressive Muscle Relaxation. James, who associated relaxation with passivity, was resistant. The technique required him to systematically tense and release every major muscle group in his body, working from feet to head. Twenty minutes, daily. Sounded both simple and pointless.
Within three weeks, his night guard stopped showing new stress fractures. Within six weeks, his therapist noted his resting facial muscle tone — which had been measuring significantly elevated on EMG biofeedback — had dropped 40%. Within three months, he’d discontinued the muscle relaxant. His jaw no longer hurt. His headaches, which he’d blamed on “dehydration” for four years, had largely disappeared.
The tension he’d been carrying for so long it had become invisible to him had, through twenty minutes of systematic muscular attention per day, begun to release.
Progressive Muscle Relaxation (PMR) was developed by Edmund Jacobson, a physician and physiologist at the University of Chicago, starting in the 1920s. Jacobson was among the first researchers to demonstrate that psychological anxiety has specific, measurable muscular correlates — that worry and stress aren’t merely mental states but physical ones, with chronic muscular tension as their somatic signature.
His key insight: if anxiety produces muscular tension, then deliberately releasing muscular tension should reduce anxiety. And by inducing tension first, before releasing it, he found he could teach patients to recognize and release the low-level chronic tension most people carry continuously without ever noticing.
THE PHYSIOLOGICAL BASIS: WHY TENSION PRECEDES RELEASE
Progressive Muscle Relaxation’s central technique — deliberately tensing a muscle group for 5-10 seconds before releasing — seems counterintuitive. If the goal is relaxation, why create tension first? The answer lies in the physiology of muscular relaxation and a phenomenon called post-contraction inhibition.
When a muscle contracts, the Golgi tendon organs (mechanoreceptors embedded in tendons that detect tension) send inhibitory signals to the spinal cord that reduce alpha motor neuron firing — the same motor neurons driving the muscle’s contraction. This is the autogenic inhibition reflex: sustained or forceful muscular contraction triggers a reflex inhibition of that same muscle as a protective mechanism against over-contraction and tendon damage.
After a voluntary muscular contraction, this inhibitory input produces a period of reduced motor neuron excitability — a physiological facilitation of relaxation that wouldn’t be present in a muscle that hadn’t just contracted.
Additionally, the deliberate contraction forces conscious awareness of the muscle group being trained. Most people’s chronic tension is largely invisible to them — the muscles sit slightly contracted continuously, but below the threshold of conscious perception, because the nervous system has adapted to the tension as “normal.” The deliberate exaggeration of tension in PMR forces the muscle group into conscious awareness and makes the contrast between tension and release perceptible.
This perceptual learning — the ability to detect the difference between a tense muscle and a relaxed one — is a core outcome of PMR training, and it’s the mechanism by which the technique produces lasting benefit beyond the session itself: practitioners learn to detect and voluntarily release low-level tension before it accumulates to symptomatic levels.
THE RESEARCH HISTORY: FROM JACOBSON TO MODERN CLINICAL TRIALS
Edmund Jacobson’s original research, published in his 1929 book “Progressive Relaxation,” rested on meticulous electromyographic measurements demonstrating that psychological states produce detectable muscular activity, and that training in muscular relaxation produces measurable reductions in psychological tension. Technically sophisticated work for its era, using the then-new technology of clinical EMG to document the somatic dimensions of anxiety states that contemporaries regarded as purely mental.
Joseph Wolpe, the South African psychiatrist who developed systematic desensitization — the behavioral therapy for phobias that formed part of the foundation of cognitive-behavioral therapy — adapted Jacobson’s technique in the 1950s and 1960s as the relaxation component of his desensitization protocol. By pairing muscular relaxation with graded exposure to anxiety-provoking stimuli, Wolpe was operationalizing Jacobson’s insight that relaxation and anxiety are physiologically incompatible states. You cannot be simultaneously muscularly relaxed and anxiously aroused.
The modern clinical trials literature on PMR is extensive, spanning anxiety disorders, hypertension, chronic pain, insomnia, chemotherapy-related nausea, and coronary heart disease rehabilitation. A 2014 meta-analysis by Manzoni and colleagues in BMC Psychiatry examining 27 PMR studies found significant reductions in anxiety (pooled effect size d = 0.79), with effects comparable to cognitive-behavioral therapy for anxiety reduction and significantly larger than waitlist or attention-control comparisons.
Effects held at 3-6 month follow-up in the subset of studies that included follow-up assessments.
ANXIETY DISORDERS: THE STRONGEST CLINICAL APPLICATION
PMR is included in evidence-based treatment protocols for generalized anxiety disorder (GAD), specific phobias, panic disorder, and social anxiety disorder in virtually every major clinical psychology guideline. In CBT for GAD, PMR is typically the first skill taught — before cognitive restructuring, worry exposure, or any other component — because reducing baseline physiological arousal creates conditions in which cognitive skills apply more effectively.
An anxious body is a body with a brain running on sympathetic activation, and cognitive strategies applied to a brain in sympathetic overdrive are like trying to do algebra on a computer that’s already running too hot. PMR cools the hardware before asking the cognitive software to perform.
A 2013 Cochrane review of relaxation therapy (PMR being the most studied modality) for anxiety disorders found significant evidence for PMR’s effectiveness across GAD, test anxiety, and dental anxiety, with effect sizes generally in the moderate-to-large range. For GAD specifically — a chronic condition marked by persistent, uncontrollable worry accompanied by physical symptoms including muscle tension, fatigue, irritability, and sleep disturbance — PMR addresses the somatic component of anxiety that cognitive restructuring alone can’t fully reach.
The muscle tension-anxiety feedback loop sits at the center of GAD’s maintenance. Worry produces muscle tension; muscle tension produces physical discomfort and hypervigilance; physical discomfort and hypervigilance provide additional triggers for worry; the cycle amplifies and sustains itself. PMR interrupts this loop at the somatic level, reducing the physiological substrate of anxious arousal and thereby reducing the internal cues that trigger and maintain worry.
Combined with cognitive therapy (which addresses the cognitive component of the loop), PMR and cognitive restructuring together produce better GAD outcomes than either alone — a finding consistently documented in component analysis studies.
“Muscle relaxation is not a passive intervention. Done correctly, it requires the same quality of deliberate attention as meditation and produces comparable neurophysiological effects through a different mechanism. The mistake is to think of it as something you do to your body while your mind is elsewhere.” — Dr. Douglas Bernstein, co-author of “Progressive Relaxation Training: A Manual for the Helping Professions.”
HYPERTENSION: THE CARDIOVASCULAR EVIDENCE
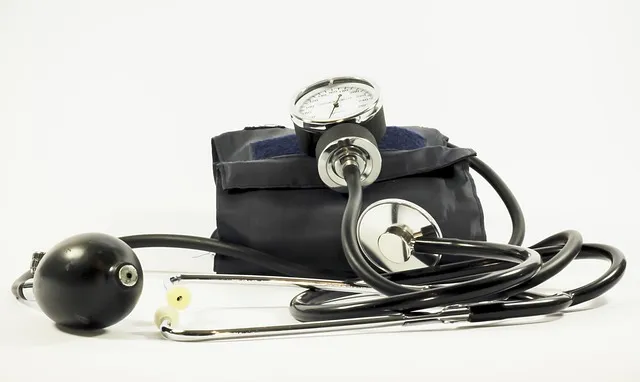
For PMR specifically, a 2017 meta-analysis by Itkonen and colleagues examining 12 RCTs found PMR produced mean reductions of 8.7 mmHg systolic and 5.3 mmHg diastolic blood pressure compared to waitlist or usual-care controls.
Clinically significant effects, these — the Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure identifies a 5 mmHg reduction in systolic blood pressure as associated with a 14% reduction in stroke risk and a 9% reduction in coronary heart disease risk at the population level.
The mechanism behind PMR’s antihypertensive effects runs through multiple pathways. Direct reduction of vascular smooth muscle tone (via parasympathetic activation and reduced catecholamine levels) lowers peripheral vascular resistance. Improved baroreflex sensitivity — the efficiency of the autonomic system’s blood pressure regulation — is consistently documented following regular PMR practice. Cortisol reduction decreases the vasoconstrictive and sodium-retaining effects of chronic HPA activation.
And improved sleep quality (discussed below) reduces the nighttime hypertension that is one of the strongest predictors of cardiovascular event risk.
CHRONIC PAIN: BREAKING THE TENSION-PAIN CYCLE
Chronic pain and muscular tension maintain each other in a physiological feedback loop that PMR is uniquely positioned to interrupt. Pain produces protective muscular guarding — reflexive contraction of muscles around the painful area as a protective mechanism. Chronic guarding produces secondary muscular pain from the sustained contraction itself. This secondary muscular pain produces additional anxiety, which increases central sensitization (the amplification of pain signals in the spinal cord and brain), which further increases pain perception and further drives guarding.
By the time a patient presents with chronic low back pain, neck pain, or headache, the original tissue damage may have healed, but the muscular tension and central sensitization cycle may be maintaining significant pain on its own.
A 2016 systematic review by Kwekkeboom and Gretarsdottir in the Journal of Pain and Symptom Management examined PMR specifically for cancer-related pain and found consistent evidence for pain reduction across multiple cancer types and treatment contexts. Effect sizes for pain were moderate (d ≈ 0.45), clinically meaningful given that these patients were receiving concurrent opioid analgesia and PMR was producing additional benefit on top of maximum conventional pharmacological management.
For tension-type headache — a condition almost definitionally related to chronic muscular tension in the neck, upper back, and pericranial muscles — PMR has particularly strong evidence. A 2010 Cochrane review by Nestoriuc and colleagues examining psychological treatments for tension headache found PMR among the best-supported non-pharmacological interventions, producing headache frequency reductions averaging 46% compared to waitlist controls.
EMG biofeedback enhanced PMR’s effects, suggesting that combining relaxation training with real-time feedback on muscular activity produces larger benefits than either alone.
INSOMNIA: THE PHYSIOLOGICAL DOOR TO SLEEP
Insomnia disorder — chronic difficulty falling or staying asleep, producing daytime impairment — is characterized by two forms of hyperarousal that interact and maintain each other: cognitive hyperarousal (racing thoughts, worry about sleep, hypervigilance to sleep-related stimuli) and physiological hyperarousal (elevated cortisol, higher resting heart rate, elevated body temperature, increased skeletal muscle tension).
PMR addresses the physiological component directly, and by reducing physiological arousal, creates conditions in which the cognitive hyperarousal is easier to address through the cognitive components of CBT-I.
Multiple meta-analyses have supported PMR as an effective insomnia treatment. The 2006 Morin et al. meta-analysis published in Sleep examined 37 treatment studies and found relaxation therapies (PMR included) produced significant improvements in sleep onset latency, wake after sleep onset, total sleep time, and sleep quality — effects that held at 3-12 month follow-up.
Relaxation therapies performed better for physiological arousal-driven insomnia (difficulty getting the body settled before bed) than for sleep maintenance insomnia (middle-of-the-night waking), where cognitive components and sleep restriction therapy produce larger effects. This specificity makes clinical sense: PMR targets the physiological pathway to sleep onset rather than the circadian or homeostatic sleep drive, which governs sleep maintenance.
ONCOLOGY APPLICATIONS: PMR DURING CANCER TREATMENT

Anticipatory nausea and vomiting — a conditioned response in which patients develop nausea before chemotherapy sessions in response to environmental cues (the clinic smell, the nurse’s face, the sight of the IV) — is particularly amenable to PMR treatment because it’s fundamentally an anxiety-conditioned phenomenon. By reducing the anxiety response driving the conditioned autonomic reaction, PMR effectively prevents the anticipatory vomiting that antiemetic medications don’t fully control.
A 1988 RCT by Burish and colleagues found PMR plus guided imagery eliminated anticipatory nausea in 75% of patients who received it, compared to 15% in the control group — a finding so dramatic it motivated widespread adoption of relaxation-based protocols in oncology nursing practice.
THE TECHNIQUE IN PRACTICE: A COMPLETE GUIDE
The standard PMR protocol, based on Bernstein and Borkovec’s 1973 training manual that remains the gold standard for clinical implementation, involves 16 major muscle groups worked through in sequence. The sequence progresses from distal to proximal — feet to calves, thighs, abdomen, lower back, chest, arms, neck, and finally the face and scalp — though some practitioners use the reverse (head to feet), and there’s no strong evidence favoring either direction.
Each muscle group is tensed at roughly 70% of maximum effort for 5-7 seconds, then released suddenly and completely. The practitioner stays focused on the sensory contrast between the tension phase and the release phase for 20-30 seconds before moving to the next muscle group. Verbal self-instruction — “letting go,” “releasing,” “noticing the difference” — can facilitate the perceptual learning component during early practice.
The complete 16-group protocol takes roughly 20-30 minutes initially; with practice, an abbreviated 7-group protocol achieves similar results in 10-15 minutes, and expert practitioners can reach a general body scan relaxation in 3-5 minutes through what Bernstein calls “recall” — recalling and recreating the relaxed state without the tension component.
Common mistakes include excessive tension (tensing to 100% rather than 70%, risking muscle strain or cramping), insufficient release time (rushing from one group to the next without fully experiencing the release phase), and practicing during acute stress (when cognitive load competes with the interoceptive focus the technique requires).
The technique works best practiced in a supine position with eyes closed in a quiet environment, at least initially — once learned, it adapts easily to seated positions for use in office or clinical settings.
Common Questions About Physiological Basis Tension ABOUT PROGRESSIVE MUSCLE RELAXATION
How quickly does PMR work?
Most people experience some reduction in muscle tension and subjective relaxation after their first session, though the effects run modest and inconsistent at first. Reliable, predictable effects on anxiety and physiological arousal develop over 2-4 weeks of daily practice (typically 15-20 minutes per session). The clinical research showing meaningful effects on anxiety disorders and blood pressure uses 8-12 week programs, suggesting that’s the timeframe for clinically significant lasting change.
The pattern mirrors other skill acquisition: early practice is effortful with inconsistent results; regular practice over weeks produces reliable, efficient, and increasingly generalized benefit.
Is PMR suitable for people with chronic pain?
Yes, with appropriate modification. The standard technique of tensing each muscle group should be adapted to avoid exacerbating pain — the tension level should be reduced to whatever is comfortable (sometimes 30-40% of maximum), and muscle groups near acutely painful areas may initially be bypassed entirely. The focus in pain patients is on developing the perceptual contrast between any level of tension and release, not on achieving the maximum tension healthy subjects tolerate.
Research in fibromyalgia, arthritis, and cancer pain consistently finds significant benefit even with modified protocols. Clinicians working with complex pain patients often pair PMR with biofeedback to provide objective confirmation that the technique is producing measurable muscle tension reductions, particularly in early practice when patients may doubt their ability to relax.
How does PMR differ from body scan meditation?
Body scan meditation involves moving attention systematically through the body with non-reactive, observational awareness — noticing whatever sensations are present without trying to change them. PMR involves actively manipulating the physical state of each muscle group — tensing and releasing — as well as attending to the result. Body scan is primarily a perceptual practice; PMR is both a perceptual and a physical manipulation practice.
The body scan’s non-reactive stance cultivates equanimity toward whatever sensation is present (including tension and discomfort); PMR’s active manipulation directly reduces tension rather than merely observing it. For clinical anxiety with prominent somatic symptoms, the active muscle regulation of PMR appears to produce faster initial benefit; for long-term mindfulness cultivation and acceptance-based coping with chronic conditions, body scan may be more therapeutically oriented.
Can PMR be combined with biofeedback for enhanced effectiveness?
Yes, and the evidence strongly supports this combination. Electromyographic (EMG) biofeedback provides real-time visual or auditory feedback on muscle electrical activity, letting practitioners observe the effects of their relaxation attempts objectively and identify residual tension that subjective perception misses. A 2019 meta-analysis by Nestoriuc and colleagues found EMG biofeedback combined with PMR produced effect sizes roughly 30% larger than PMR alone for tension headache, anxiety, and blood pressure outcomes.
The combination proves particularly valuable during learning, when patients often overestimate their ability to relax and objective feedback corrects this misperception, accelerating skill acquisition. Once the skill is established, biofeedback becomes less essential — the learned interoceptive accuracy allows independent self-monitoring.
Are there any contraindications for PMR?
PMR has an excellent safety profile for the great majority of individuals. Active muscle injuries or acute inflammation are local contraindications — specific muscle groups near injuries should be bypassed or only gently engaged. Severe cardiovascular disease (recent MI, unstable angina, severe heart failure) warrants medical clearance before beginning any tension-release protocol, though the modest cardiovascular stress of 70% tension applied to peripheral muscle groups is substantially lower than that of most conventional exercise.
Psychosis and dissociative disorders are relative contraindications — the intense interoceptive focus of PMR can be disorienting for individuals with fragile reality-testing or dissociative symptoms. Individuals with complex trauma histories should approach PMR with a therapist’s guidance, since the increased body awareness can sometimes activate trauma material. For otherwise healthy adults with anxiety, pain, insomnia, or hypertension, PMR is among the safest effective interventions available.
THE NEUROSCIENCE BEHIND PMR: BRAIN IMAGING EVIDENCE

The authors hypothesized that PMR reduces amygdala reactivity partly through the enhanced parasympathetic tone its physiological effects produce (vagal activation dampens amygdala excitability through known neurophysiological pathways) and partly through a learned cognitive reassociation between somatic sensations and safety — the repeated pairing of bodily awareness with relaxation and relief, rather than with anxiety and threat.
EEG studies during PMR consistently show shifts from beta-wave (activated, alert processing) toward alpha-wave dominance (relaxed, unfocused awareness) during the relaxation phase following muscle group release. The alpha-wave shift is particularly prominent in prefrontal regions, consistent with the reduced anxious vigilance and cognitive self-monitoring practitioners report. Heart rate variability increases during PMR sessions, confirming parasympathetic activation, and this HRV increase persists for 30-60 minutes post-session — extending the physiological benefit well beyond the formal practice period.
The interaction between PMR’s somatic focus and the brain’s default mode network is an underexplored area with real theoretical importance. The interoceptive attention of PMR — the deliberate tracking of physical sensations throughout the body — engages the posterior insula and primary somatosensory cortex in a pattern that occupies cognitive resources otherwise available for default mode self-referential processing.
Like walking meditation and seated body scan, PMR appears to produce DMN quieting through occupying attention with present-moment body awareness, reducing the ruminative processing the DMN generates when attention sits unoccupied.
PMR ACROSS THE LIFESPAN: PEDIATRIC AND GERIATRIC APPLICATIONS
PMR has been studied and adapted for use across the full age range, from school-age children to elderly populations. In pediatric applications, PMR for test anxiety and school-related stress is among the best-supported non-pharmacological interventions available.
A 2016 systematic review examining PMR in children aged 6-18 found consistent improvements in academic test anxiety, trait anxiety, and behavioral indicators of stress, with protocols adapted to developmental level (shorter sessions, playful framing of the tension-release phases as “squeezing lemons” or “making muscles like a superhero”) producing comparable efficacy to adult protocols with appropriate modifications.
For pediatric ADHD, PMR has shown preliminary efficacy in reducing behavioral symptoms of hyperactivity and improving classroom attention across several small RCTs. The mechanism proposed: the deliberate somatic attention of PMR practices precisely the inhibitory control that ADHD deficits — which involve reduced prefrontal inhibition of impulse and attentional capture by salient stimuli — most require.
PMR teaches the child to notice an impulse (the tension) and choose a response (the release) rather than acting on it automatically — embodied executive function training, essentially.
In older adults, PMR for anxiety, insomnia, and hypertension is well supported by research in geriatric populations. Adaptations for physical limitations — shorter sessions, reduced tension intensity, avoidance of muscle groups near arthritic or injured areas — maintain efficacy while improving safety and tolerability.
A distinctive application in geriatric care is PMR for fear of falling: the chronic muscular tension associated with fall-related anxiety creates a paradoxically higher fall risk (tense muscles are less responsive to perturbation, and preoccupation with fall risk reduces the attentional resources available for the balance monitoring that prevents falls).
PMR training that reduces this anxiety-driven tension has been shown to reduce fall incidence in several geriatric care studies, offering a behavioral complement to the balance exercise programs most fall prevention programs emphasize.
James Benson — the attorney who opened this story with a stress-fractured molar — eventually became the person in his office who’d mention progressive muscle relaxation to junior associates visibly coiling under deadline pressure. Not because he’d turned into a wellness evangelist, but because the technique had been specific, practical, and measurably effective for him in a way that seemed worth passing on. He didn’t call it self-care. He called it taking your nervous system out of overdrive.
His jaw never fractured another molar. The tension he’d carried as though it were part of his identity turned out to be optional. Of all the possible revelations a 28-year-old attorney might stumble into, that’s one of the more practically useful ones.
INTEGRATING PMR WITH OTHER TREATMENTS: THE SYNERGY EVIDENCE
PMR rarely operates in clinical isolation. The most effective clinical protocols combine it with complementary interventions addressing dimensions of the target condition that PMR alone can’t fully reach. Understanding these synergies helps clinicians and self-directed practitioners get more out of the technique.
PMR plus cognitive therapy for anxiety produces consistently better outcomes than either alone. The mechanism is straightforward: cognitive therapy targets the thought patterns (catastrophizing, overestimation of threat, underestimation of coping) that generate and maintain anxious arousal; PMR reduces the physiological arousal that makes those thought patterns feel true and urgent. A well-rested, physiologically calm brain can evaluate evidence for catastrophic beliefs more accurately than an aroused one.
Meta-analyses examining CBT component analyses consistently find that adding PMR to cognitive restructuring produces larger effect sizes than either component used alone.
PMR plus sleep hygiene for insomnia is a well-validated combination. Sleep hygiene (consistent sleep schedule, dark room, avoiding caffeine, screens, and large meals before bed) addresses the circadian and behavioral factors maintaining insomnia; PMR addresses the physiological hyperarousal that prevents sleep onset even when sleep hygiene is good. Sleep restriction therapy (the core of CBT-I) consolidates sleep drive but produces significant early-treatment distress; PMR helps patients tolerate this distress by reducing the physiological anxiety of lying awake.
The combination of all three components — sleep restriction, sleep hygiene, and PMR — makes up the multicomponent CBT-I that remains the gold standard for insomnia treatment.
PMR plus biofeedback amplifies outcomes through the learning enhancement objective feedback provides. Standard EMG biofeedback units display muscle electrical activity in real time — a tone or visual display that rises with tension and falls with relaxation. The immediate, objective confirmation that a relaxation attempt is producing measurable muscle tension reduction accelerates skill acquisition, corrects overestimates of relaxation achievement, and provides motivation through visible progress.
For clinical applications where speed of skill acquisition matters — acute anxiety episodes, pre-procedural preparation, intensive pain rehabilitation — the biofeedback-enhanced version of PMR should be the first choice.
PMR plus medication for anxiety and hypertension is a common combination in clinical practice, and the evidence suggests it’s both safe and synergistic. PMR reduces the physiological substrates of both conditions through mechanisms independent of the pharmacological mechanisms of most anxiolytics and antihypertensives — meaning the combination produces additive rather than redundant benefit.
More clinically significant is the evidence from several RCTs that sustained PMR practice allows medication reduction in both conditions: patients who maintain regular practice for 6-12 months often achieve adequate anxiety or blood pressure control with lower medication doses. Not an argument for unilateral medication discontinuation — but it does suggest prescribing physicians should reassess medication requirements in patients who’ve established consistent PMR practice, since the physiological targets of the medication may have shifted.
THE ECONOMICS OF PMR: COST-EFFECTIVENESS ANALYSIS
PMR’s cost-effectiveness matters for clinical decision-making in healthcare systems operating under resource constraints, and the analysis is compelling. The technique can be learned from a book (Bernstein and Borkovec’s training manual, widely available), from a group class (typically 6-8 sessions at community health centers), or from a single individual session with a psychologist or physical therapist — a dramatically lower cost than the pharmacological, surgical, and specialist medical options it can supplement or partially replace.
A health economics analysis by Smith and colleagues (2019) examining PMR as an adjunct to antihypertensive pharmacotherapy found that 12 weeks of group PMR training followed by independent maintenance practice was associated with medication cost savings of roughly $380 per patient per year (through reduced need for second or third antihypertensive agents), against a delivery cost of roughly $120 per patient — a 3:1 return on investment that would be considered excellent for any healthcare intervention.
For chronic pain management, the cost savings run potentially larger. Chronic pain management commonly involves combinations of opioid analgesics, NSAIDs, muscle relaxants, antidepressants, physical therapy, specialist consultations, and imaging studies — a complex, expensive management package. Studies showing PMR-induced reductions in pain intensity and analgesic use suggest that widespread integration of PMR into chronic pain management could produce substantial system-level cost savings while improving outcomes.
The barrier isn’t the evidence. It’s the difficulty of implementing behavioral interventions in healthcare systems built around pharmaceutical and procedural reimbursement models. Changing those models is a policy challenge beyond any individual clinical decision, but the clinical opportunity is clear and the economic case is strong.
PMR VERSUS OTHER RELAXATION TECHNIQUES: COMPARATIVE EFFECTIVENESS
A recurring clinical question is how PMR compares to other relaxation and mind-body techniques for specific applications. The comparative effectiveness literature offers useful, if imperfect, guidance. For anxiety disorders, PMR and autogenic training produce comparable outcomes in most head-to-head studies, with AT showing slight advantages for somatic anxiety symptoms and PMR showing slight advantages for musculoskeletal tension and headache. For insomnia, sleep hygiene education produces faster results for behavioral sleep disorders, while PMR outperforms it for physiologically hyperaroused insomnia.
For chronic pain, mindfulness-based interventions show advantages over PMR for central sensitization syndromes (fibromyalgia, chronic widespread pain) where cognitive and attentional mechanisms are the primary drivers, while PMR shows comparable or superior effects for conditions with prominent muscular tension components (tension headache, neck pain, TMJ disorder).
Against pharmacological comparators, PMR consistently shows favorable risk-benefit profiles in anxiety and insomnia. Against benzodiazepines — the most commonly prescribed anxiolytics and sleep medications — PMR produces smaller short-term effects but avoids the risks of dependence, tolerance, cognitive impairment, fall risk in older adults, and withdrawal symptoms that make long-term benzodiazepine use problematic.
A 2016 Cochrane review concluded that psychological interventions including PMR should be offered as alternatives or adjuncts to benzodiazepines in the treatment of anxiety and insomnia, given their comparable efficacy and dramatically superior safety profile for long-term use.
The practical recommendation for most people approaching PMR for the first time is to start with it for any condition involving prominent muscular tension, anxiety, insomnia, or hypertension — the combination of strong evidence, near-zero cost, and excellent safety makes it an appropriate first choice before considering pharmacological or more complex interventions.
If PMR alone proves insufficient after a six-to-eight-week trial with consistent daily practice, it then provides an excellent foundation on which to layer cognitive therapy, biofeedback, or medication as needed.
The sequence — behavioral intervention first, additional intervention layers only as needed — isn’t only cost-effective. It often produces better long-term outcomes than pharmacology-first approaches, because it builds the self-regulatory skills that determine long-term functional capacity, rather than substituting an external agent for developing those skills.
The case for Progressive Muscle Relaxation ultimately rests on something simple: the body and mind are not separate systems operating in parallel, and interventions that treat them as if they are will always leave half the problem unaddressed. Jacobson understood this in the 1920s. The clinical trials have confirmed it, condition by condition, decade by decade.
The technique is a century old, costs nothing, requires no equipment, has no serious side effects, and produces measurable changes in the physiology of anxiety, pain, and cardiovascular disease. Its obscurity relative to its evidence base is one of the stranger facts about modern medicine. Its accessibility is the most important thing about it.
The Practical Framework: Applying Physiological Basis Tension Precedes In Real Life
References
Editorial StandardsCorrectionsMedical DisclaimerAbout Our ContentAffiliate DisclosureSite Map