
He sat on the edge of the bed listening to his wife breathe, steady and undisturbed, and thought about everything he’d been promised: more energy, better focus, lower blood pressure, a longer life. What he actually got was a red groove across his nose every morning, three sinus infections, and a marriage under quiet strain because the machine’s white noise kept her from sleeping deeply.
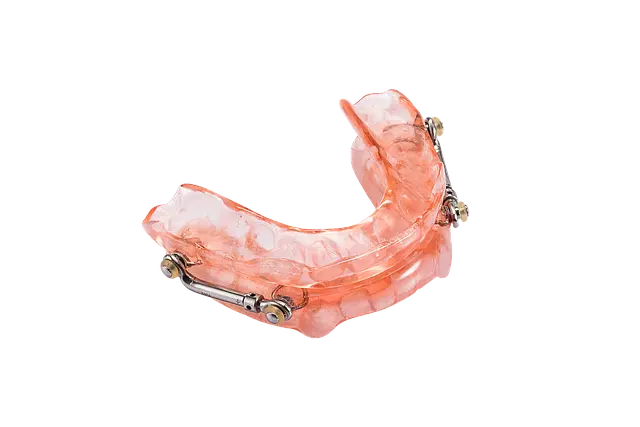
His sleep physician, to her credit, didn’t lecture him. She slid a small device across her desk — a custom-fitted oral appliance, something between a mouthguard and a retainer — and said, “About forty percent of my CPAP-intolerant patients end up here eventually. Some of them wish they’d started here.”
Marcus’s story is not unusual. An estimated 30 to 50 million Americans have obstructive sleep apnea, a condition in which the soft tissues of the throat repeatedly collapse during sleep, blocking the airway and triggering micro-arousals that shred sleep architecture without the person ever fully waking. CPAP — continuous positive airway pressure — remains the clinical gold standard. For good reason. It works.
But adherence rates are consistently reported between 30 and 60 percent at the one-year mark, depending on how adherence gets defined. A machine gathering dust on the nightstand is treating nobody.
Oral appliance therapy (OAT) entered the mainstream not as a replacement for CPAP but as a credible alternative — one with a genuinely different mechanism, a different evidence base, a different set of trade-offs. Worth understanding what it is, who it works for, and what the evidence actually reveals.
The therapy someone actually uses beats the therapy they abandon. Every time.
What Oral Appliances Actually Do to Your Airway
The physics of obstructive sleep apnea are straightforward even if the biology isn’t. Falling asleep drops muscle tone throughout the body — including the muscles holding the pharyngeal airway open. In people with OSA, that relaxation tips into collapse. The tongue, soft palate, and lateral pharyngeal walls fall inward, narrowing or completely occluding the airway.
The brain detects rising carbon dioxide and plummeting oxygen, fires an arousal signal, muscle tone briefly returns, the airway reopens — and the cycle starts over. Sometimes hundreds of times a night.
Mandibular advancement devices (MADs), the most common form of oral appliance for OSA, interrupt this cycle mechanically. By holding the lower jaw (mandible) in a protruded position — typically 5 to 10 millimeters forward of its natural resting position — the device stretches the soft tissues of the pharynx, particularly the genioglossus muscle of the tongue.
This mechanical tension increases the cross-sectional area of the upper airway and makes it less prone to collapse under the reduced muscle tone of sleep.
MRI and endoscopy studies have confirmed what the mechanism predicts. A 2015 study published in Sleep using upper airway MRI during sleep found that MAD therapy increased the retropalatal airway area by an average of 20 percent and the retroglossal area by 18 percent. The palate itself was elevated and the lateral walls drawn outward.
Not subtle changes. Geometrically meaningful increases in the tube a person breathes through all night, every night, for the rest of their life if the condition goes untreated.
The second major category of oral appliance is the tongue-retaining device (TRD), which uses a small suction bulb at the front to hold the tongue forward regardless of jaw position. TRDs are less commonly used but have specific applications in patients with jaw joint issues that preclude mandibular advancement, or in those with significant macroglossia — an enlarged tongue that is the primary anatomical contributor to their airway obstruction.
The evidence base for TRDs is thinner than for MADs but growing steadily as the technology improves.
Custom-fabricated MADs are made from impressions of the patient’s teeth and adjusted over a series of appointments using calibrated titration screws. The goal: find the minimum effective protrusion — enough to open the airway, not so much that it strains the temporomandibular joint or causes significant muscle soreness.
This titration process typically takes four to twelve weeks, and it’s a substantial part of why outcomes with dental sleep medicine differ so markedly from outcomes with over-the-counter mouthguards — which are neither fitted nor titrated and cannot maintain consistent protrusion as muscles relax during sleep.
The airway anatomy relevant to MAD function extends beyond the jaw. The hyoid bone — a horseshoe-shaped bone in the throat to which numerous muscles attach — is mechanically connected to the mandible, and mandibular advancement pulls the hyoid anteriorly, which in turn pulls the tongue base forward and enlarges the retroglossal space.
Patients with a more posteriorly positioned hyoid bone, a common anatomical finding in OSA, tend to respond particularly well to mandibular advancement because the mechanics are more favorable. Lateral cephalometric X-ray analysis that includes hyoid position has become standard practice in advanced dental sleep medicine evaluation.
The Evidence Base: What the Trials Actually Show
The comparison between CPAP and oral appliance therapy is one of the most studied questions in sleep medicine, and the findings are more detailed than either camp typically acknowledges. Short version: CPAP reduces the apnea-hypopnea index more thoroughly, but oral appliances produce comparable or sometimes superior outcomes on the health endpoints that actually matter to patients living with the disease.
The AHI — the number of breathing interruptions per hour of sleep — is the primary metric in most sleep apnea research. A 2015 meta-analysis in JAMA Internal Medicine analyzing 51 randomized trials found that CPAP reduced AHI by approximately 13 events per hour more than oral appliances on average. AHI normalization rates — getting patients below 5 events per hour — were achieved in roughly 60 to 70 percent of MAD patients versus 90 percent of CPAP patients.
CPAP is a more complete airway treatment on this metric. Nobody should pretend otherwise, and no honest clinician does.
But the same meta-analysis found something that upends simple hierarchies: on daytime sleepiness as measured by the Epworth Sleepiness Scale, blood pressure reduction, quality of life measures, and patient preference, oral appliances performed equivalently to CPAP — and on some measures, better. The paradox has a straightforward explanation, once stated.
CPAP is used, on average, about four to five hours per night among patients counted as “adherent.” Oral appliances are worn approximately seven hours per night. Moderate treatment applied across the entire sleep period can outperform superior treatment applied to only part of it. The biological effects on blood pressure and daytime function are driven by cumulative hours of airway protection, not by a device’s theoretical ceiling.
A landmark 2013 randomized crossover trial by Gagnadoux and colleagues, published in JAMA, directly compared outcomes in 56 patients with moderate-to-severe OSA randomized to three months each of CPAP and MAD therapy. Despite CPAP achieving better AHI reduction, 24-hour ambulatory blood pressure was equivalently reduced by both devices. Endothelial function, assessed by flow-mediated dilation of the brachial artery — a validated marker of cardiovascular health — also showed no significant difference between the two treatments.
The authors concluded that oral appliances were “a legitimate first-line therapy” for mild to moderate OSA and “a viable alternative” even in severe disease for patients who cannot or will not use CPAP.
The cardiovascular stakes here deserve emphasis that clinical conversations sometimes skip past. A 2019 prospective cohort study in Journal of the American College of Cardiology following 1,023 patients over 10 years found that untreated OSA was associated with a 2.3-fold increase in major cardiovascular events including myocardial infarction, stroke, and cardiovascular death. Patients who received any form of effective treatment — CPAP or oral appliance — had event rates comparable to matched controls without OSA.
Treatment modality mattered less than whether treatment happened at all, and happened consistently. This finding has been replicated across multiple large cohort studies and is about as close to settled as observational data gets in sleep medicine.
Cognitive function data has been messier, but a 2020 systematic review in Sleep Medicine Reviews examining 18 trials found that both CPAP and MAD therapy improved objective cognitive measures — sustained attention, executive function, working memory — compared to sham treatment or no treatment. Effect sizes were similar between devices once use hours were controlled for, which again points to adherence as the variable that matters, not device superiority.
Who Is a Good Candidate — and Who Isn’t
Oral appliance therapy is not for everyone. The honest conversation about candidacy involves several intersecting factors: OSA severity, craniofacial anatomy, dental health, jaw joint status, and — critically — what the patient will actually wear consistently over months and years.
Severity guidelines have evolved considerably over the past decade. The American Academy of Sleep Medicine’s 2015 clinical practice guidelines recommend oral appliances as a first-line treatment for mild to moderate OSA (AHI 5 to 30) and as an acceptable alternative for severe OSA (AHI above 30) in patients who prefer them or cannot tolerate CPAP.
That’s a more permissive stance than the field held a decade earlier, and it reflects accumulating evidence that even in severe cases, many patients with favorable anatomy achieve adequate control with well-fitted, properly titrated appliances. The 2019 update to these guidelines didn’t substantially change that position.
Body mass index is a significant modifying factor. A 2017 meta-regression analysis found that treatment response with MADs was significantly better in patients with BMI under 30 compared to those with BMI above 35. Obesity increases the adipose tissue surrounding the pharynx — deposits in the lateral pharyngeal walls, the tongue base, the parapharyngeal fat pads — and the mechanical advantage of mandibular advancement isn’t enough to overcome that burden in some heavier patients.
That doesn’t mean patients with elevated BMI can’t benefit; many do, substantially. But the probability of complete AHI normalization is lower, the possibility of inadequate control higher, and the conversation about supplementary or alternative interventions should happen proactively — not after several months of suboptimal treatment.
Craniofacial anatomy is perhaps the single most predictive factor for response. Patients with retrognathia — a posteriorly positioned lower jaw — tend to respond exceptionally well because mandibular advancement pulls the jaw toward a more neutral position relative to the upper jaw. The airway benefits are disproportionate to the amount of advancement. Patients with a high, narrow palate, significant nasal obstruction, or a short and thick neck may see more variable results.
A lateral cephalometric radiograph — an X-ray showing the complete side profile of the skull from hair to chin — gives experienced clinicians the anatomical information to estimate probability of response and plan a titration strategy.
Dental prerequisites are strict. The patient needs enough healthy teeth to anchor the appliance — most designs require at least eight to ten teeth per arch in good periodontal condition. Active periodontal disease (loose teeth, bone loss) is a relative contraindication because retention forces can accelerate tooth mobility. Active bruxism complicates things further: severe bruxers can crack or deform appliances within months, and grinding forces are substantial enough to accelerate occlusal changes.
Hybrid designs incorporating features of both occlusal splints and mandibular advancement devices have been developed specifically for this population.
Temporomandibular joint health is the most commonly cited contraindication and the one most subject to clinical judgment. Patients with active TMJ disorder characterized by locking, acute inflammatory arthritis, or severe pain are genuinely poor candidates for standard mandibular advancement, since prolonged protrusion can worsen joint symptoms. But “TMJ disorder” covers everything from minor clicking without pain to degenerative joint disease, and plenty of patients with mild or historical symptoms use oral appliances successfully with careful titration and close monitoring.
A blanket exclusion based on any TMJ history is more conservative than the evidence requires.
Custom vs. Over-the-Counter: Why This Distinction Matters Enormously

Custom-fabricated appliances are made from digital or physical impressions of the patient’s specific dentition, ensuring precise fit, retention, and load distribution across the teeth. They’re adjustable in small increments — typically 0.25 to 0.5 millimeter per adjustment — letting the clinician titrate mandibular advancement to the minimum effective dose for that patient’s specific anatomy. The retention means the device holds its position all night.
The titration capability means protrusion can be refined based on objective sleep testing. None of this is a luxury feature. These are functional requirements for the thing to actually work.
Over-the-counter devices are none of the above. A 2016 study in Chest directly compared a custom-fitted MAD against a self-fitted thermoplastic device in 100 patients with mild to moderate OSA. The custom device reduced AHI by 51 percent; the OTC device reduced it by 22 percent. On the Epworth Sleepiness Scale, the custom device produced a 3.8-point reduction; the OTC produced 1.2 points.
Researchers also noted more jaw discomfort, more morning occlusal changes, and more early discontinuation with the OTC devices. On every outcome that mattered clinically, the custom device won, and won clearly.
The mechanism behind that gap isn’t mysterious. A poorly fitting device can’t consistently maintain its intended protrusion through the night. During the initial phase of sleep, when muscle tone is partially preserved, the appliance stays in position through mild clenching. As the night progresses and muscle tone falls, a loosely fitting device gradually shifts, reducing its therapeutic effect at exactly the moment — REM sleep and deep N3 sleep — when it’s needed most.
Custom devices with tight retention and calibrated protrusion hold their position regardless of muscle tone. Which is why they work when over-the-counter devices don’t.
Insurance coverage has historically been uneven but has improved substantially over the past decade. Medicare covers oral appliances under durable medical equipment codes E0485 and E0486, and most major commercial insurers provide coverage with appropriate documentation.
The out-of-pocket math differs patient to patient, plan to plan, but the comparison should always be made over a multi-year horizon — and it should include the full ongoing costs of CPAP: the machine, multiple mask systems, tubing, filters, humidifier components, periodic replacements. Those accumulate to $400 to $700 per year beyond the initial equipment cost.
The Side Effect Landscape — Honest, Not Sanitized
Oral appliance therapy has a side effect profile generally milder than CPAP’s, but not trivial — and honest informed consent means discussing it clearly before treatment starts rather than minimizing it to secure buy-in. Patients surprised by side effects tend to quit. Patients warned about them tend to tolerate them as an expected feature of early treatment.
Morning jaw soreness affects approximately 70 percent of patients during the first month and typically diminishes as the masticatory muscles adapt to the mandible’s new resting position. The soreness is usually described as a dull ache in the masseter or pterygoid muscles — similar to how muscles feel after unaccustomed exercise. It tends to resolve within 15 to 30 minutes of waking.
Persistent or worsening jaw soreness signals that protrusion has advanced too quickly or too far. The correct clinical response: back off titration by one to two increments and allow more adaptation time before resuming advancement.
The most clinically significant long-term side effect is occlusal change — shifts in the relationship between upper and lower teeth that can become permanent with prolonged use. A 2014 seven-year longitudinal study by Marklund and colleagues, following patients who had used MADs for an average of 7.4 years, found that 87 percent experienced some degree of bite change.
The most common changes were reduced overbite (the vertical overlap of the upper teeth over the lower) and reduced overjet (the horizontal protrusion of the upper teeth). For most patients these changes were minor — one to two millimeters, not clinically symptomatic. For approximately 14 percent, changes were clinically significant and required dental intervention. The risk is real, ongoing, and cumulative with years of use.
Morning repositioning exercises reduce but don’t eliminate occlusal change risk. The standard protocol: remove the device upon waking and immediately perform a series of jaw exercises — closing firmly, moving the jaw laterally, biting into a soft repositioner — designed to stimulate the periodontal ligaments and return the condyles to their natural position before eating or speaking. Research shows approximately 40 percent reduction in occlusal change with consistent morning repositioning compared to device use without exercises.
TMJ symptoms develop in a minority of patients — 5 to 15 percent based on a 2018 systematic review — and most cases resolve after device adjustment or temporary discontinuation. The causal pathway is almost always the same: excessive protrusion, advanced too fast. Joint symptoms are rarely the result of an inherent incompatibility between mandibular advancement and a specific patient’s joint. Almost always it’s just moving too fast.
Experienced dental sleep medicine providers adjust titration rate based on patient response, checking in weekly by phone or app rather than waiting for scheduled appointments.
The Titration Process: Patience as a Clinical Requirement
One of the most consistent predictors of oral appliance success is how carefully the titration process gets managed — and how patient both clinician and patient are willing to be. Rushing titration is the single most reliable path to side effects, premature device abandonment, and suboptimal long-term outcomes. This is also where provider quality differences matter most, because titration requires ongoing communication, judgment, and responsiveness that no protocol can fully substitute for.
Initial protrusion is typically set at 50 to 75 percent of maximum protrusion during the first fitting. The device should be comfortable enough for a full night’s wear from the start — the goal isn’t discomfort tolerance, it’s airway mechanics. Over subsequent weeks, the patient advances the device by 0.25 millimeters every three to seven days, guided by symptom reports.
The therapeutic range is highly individual: some patients achieve adequate airway control at 4 millimeters of advancement, others need 9 or 10. Maximum protrusion varies between patients, typically ranging from 12 to 18 millimeters.
Objective verification of treatment response is essential and sometimes neglected in practices that prioritize volume over quality. Symptom improvement — partner-reported snoring reduction, better energy — is real and meaningful but unreliable as the sole endpoint of titration. Patients with severe OSA can feel significantly better on inadequate treatment, because even partial AHI reduction improves sleep architecture enough to produce noticeable functional benefit.
A patient whose AHI dropped from 45 to 18 may feel dramatically better while still carrying significant cardiovascular risk. A home sleep apnea test or in-laboratory polysomnography with the device at its current titration position is the standard of care for confirming adequate control.
Remote titration protocols have become a meaningful quality-of-life improvement for patients navigating the weeks-long titration process. A 2020 study in Sleep found that remotely guided titration using a smartphone app tracking snoring acoustics and SpO2 produced outcomes equivalent to in-person titration while requiring significantly fewer clinic visits.
Not a cost-cutting gimmick. It genuinely allows more frequent, data-guided adjustments that improve the titration trajectory without patients taking time off work for weekly clinic visits.
Once optimal protrusion is established and confirmed by objective sleep testing, the device requires annual re-evaluation with updated sleep testing. OSA severity changes with weight fluctuation, aging-related changes in muscle tone, hormonal shifts, and nasal anatomy changes from allergies or structural changes. An appliance calibrated at 45 years old and 185 pounds may be delivering inadequate control at 58 years old and 210 pounds.
The annual re-evaluation isn’t administrative box-checking. It’s the mechanism that keeps treatment matched to the disease as both evolve.
Combination Therapy: When One Device Isn’t Enough

MAD combined with positional therapy is the most evidence-supported first combination to try. OSA severity is substantially worse in the supine position for approximately 60 percent of OSA patients — a phenomenon called positional OSA. The mechanism: gravity pulls the tongue and soft palate posteriorly when lying on the back, compounding the airway narrowing the device is trying to counteract.
A 2021 study in Journal of Clinical Sleep Medicine found that patients with positional OSA who combined a vibrotactile positional device with MAD therapy reduced their residual AHI from 12.4 to 4.1 events per hour — a normalization neither device achieved alone. Modern positional devices worn as a chest strap or collar buzz gently when supine, prompting lateral repositioning without fully waking the patient.
MAD combined with myofunctional therapy is a more time-intensive but potentially durable combination. Myofunctional therapy involves targeted exercises for the tongue, soft palate, pharyngeal walls, and jaw muscles — essentially physical therapy for the upper airway. A 2015 meta-analysis in Sleep found that myofunctional therapy alone reduced AHI by approximately 50 percent in adults and 62 percent in children. The presumed mechanism: increased muscle tone and motor coordination of the pharyngeal muscles, reducing their tendency to collapse.
In combination with mandibular advancement, the additive effect looks meaningful, though high-quality controlled combination trials remain limited.
MAD combined with nasal therapy matters particularly for patients with significant nasal resistance who haven’t been adequately evaluated for nasal obstruction. The upper airway functions as a connected hydraulic system; reducing resistance in the nasal passages reduces the total pressure gradient across the system and makes it easier to maintain pharyngeal patency.
A 2018 study found that patients treated for nasal obstruction — through corticosteroid spray, saline irrigation, or septoplasty for severe deviation — prior to MAD titration required significantly less mandibular advancement to achieve equivalent AHI reduction, with corresponding reductions in side effect burden.
For patients who have genuinely failed both CPAP and OAT with appropriate combination strategies, hypoglossal nerve stimulation — an implanted device that activates the genioglossus muscle in synchrony with the breathing cycle — represents a third-line option with strong evidence in carefully selected patients.
The Inspire device received FDA approval in 2014, and subsequent trials have shown sustained AHI reduction of greater than 75 percent at five-year follow-up in patients meeting selection criteria: BMI under 35, moderate-to-severe OSA without complete concentric collapse at the palate on drug-induced sleep endoscopy, and absence of central apnea predominance.
The Dental Sleep Medicine Specialty — Navigating Provider Qualifications
Oral appliance therapy sits at the intersection of sleep medicine and dentistry, and navigating that intersection means understanding the credentialing landscape. Not every dentist offering oral appliances has equivalent training in sleep-disordered breathing, and the quality variation across providers is significant enough to matter clinically.
A poorly managed course of OAT — wrong device selection, inadequate titration, no objective outcome verification — can produce side effects without producing benefit, leaving patients concluding that oral appliances don’t work when what actually failed was the implementation.
The American Academy of Dental Sleep Medicine (AADSM) offers the Diplomate credential (D.ABDSM), awarded after a rigorous written and oral examination covering sleep medicine, upper airway anatomy, appliance therapy, and management of side effects. Diplomates represent the highest level of specialist credentialing in this field. A second credential — the Qualified Dentist designation — is available after completing approved coursework and treating a minimum number of cases.
Both credentials require ongoing continuing education to maintain, and both are searchable through the AADSM’s online provider directory.
The practical implication for patients: seek a dentist who works collaboratively with a sleep physician, requires a physician-ordered sleep study before fitting any device, and performs objective outcome verification with a follow-up sleep test after titration is complete. Any provider willing to fit an oral appliance without a prior sleep study — based solely on partner-reported snoring or patient self-report — should be avoided.
Snoring without diagnosed OSA is a different condition from diagnosed OSA with an AHI of 35, and the treatment decision for severe disease must involve a physician who understands the cardiovascular stakes.
Collaborative care models — where the dental sleep medicine provider and the sleep physician communicate regularly, share sleep study data, and co-manage treatment decisions including when to transition to or add CPAP — produce consistently better outcomes than siloed care. The AADSM has published detailed protocols for this physician-dentist communication, and practices implementing these protocols have lower adverse event rates and better documented treatment responses than those operating independently.
Ask up front whether the dentist has a referring sleep physician relationship and how they communicate about patients.
Long-Term Adherence: What Actually Predicts Whether People Keep Using It
The stated advantage of oral appliance therapy over CPAP is adherence — or more precisely, the probability that a given patient will actually use it consistently over years. But oral appliances aren’t adherence-proof, and overpromising on this dimension sets patients up for a rude surprise when nightly device use runs into comfort limitations, travel inconvenience, and relationship dynamics.
Long-term compliance rates in published prospective studies range from 56 to 77 percent at two years and decline gradually in longer follow-up studies. Better than CPAP adherence, but not dramatically so.
Patient satisfaction in the first month is the strongest single predictor of long-term use. A 2020 study in JAMA Otolaryngology found that patients who reported high satisfaction at four weeks had a 78 percent probability of continued device use at two years; patients with low satisfaction at four weeks had a 31 percent probability. The implication is clear: the first month is when clinical investment in follow-up, troubleshooting, and titration adjustment pays its greatest dividend.
A patient who makes it through the first month with manageable symptoms and perceives functional benefit is highly likely to keep going long-term.
Bed partner satisfaction is a secondary predictor underappreciated in clinical discussions. Partners who report meaningful snoring reduction and improved sleep quality in the first weeks become active advocates for device use — they remind the patient, comment on improvement, create social reinforcement measurably associated with adherence. Partners who don’t perceive improvement, or who are bothered by the appliance’s appearance or the change in breathing sounds, create the opposite pressure.
Including bed partners in the education and follow-up process isn’t just courtesy. It’s clinically relevant behavior change strategy.
Device characteristics matter more than marketing materials acknowledge. Appliances with a smaller vertical opening between the teeth, less total bulk inside the oral cavity, and some freedom of lateral jaw movement during sleep consistently show better adherence than designs that feel maximally restrictive. The Herbst, Elastic Mandibular Advancement, and Narval CC designs, all of which permit limited lateral jaw movement, outperform rigid fixed-advancement designs on comfort and adherence metrics in direct comparisons.
The functional freedom to yawn, to briefly close the mouth more naturally, or to shift position without the jaw locked into a single rigid protrusion correlates with subjective comfort — and ultimately with whether patients choose to wear the device every night for years.
The Weight Loss Interaction and the GLP-1 Era

But OSA also promotes weight gain through multiple physiological mechanisms: sleep fragmentation disrupts leptin and ghrelin signaling, driving hyperphagia and preference for calorie-dense foods; daytime fatigue from fragmented sleep reduces spontaneous physical activity; and the nightly cortisol burden of hypoxic stress promotes visceral adiposity through glucocorticoid-mediated metabolic effects. Effective treatment of OSA creates the physiological conditions that make weight management easier — not automatic, but meaningfully easier.
Patients using oral appliances who achieve significant weight loss — through behavioral intervention, bariatric surgery, or pharmacological support — should be re-evaluated with objective sleep testing, because their required treatment may have changed substantially. Some patients who initiated MAD therapy at BMI 34 and successfully reach BMI 26 through sustained behavioral change find their OSA has resolved or reduced to mild severity manageable with positional therapy alone.
Continuing at full therapeutic protrusion in a patient whose disease has substantially remitted isn’t neutral. It continues to carry side effect risk without proportionate benefit.
The emergence of GLP-1 receptor agonists as potent weight loss agents has generated significant new interest in the OSA-metabolic interaction. The SURMOUNT-OSA trial, published in New England Journal of Medicine in 2024, found that tirzepatide produced a 55 percent reduction in AHI compared to placebo over 52 weeks in patients with OSA and obesity, with 42 percent of participants achieving AHI normalization on medication alone.
This doesn’t render oral appliances obsolete — most trial participants didn’t achieve normalization, the long-term durability of pharmacological OSA treatment is unknown, and many patients aren’t candidates for GLP-1 therapy. But it does fundamentally change the conversation about OSA treatment in patients also dealing with significant obesity. How should we treat your airway and how should we treat your metabolic health — those two questions are now inextricably linked.
Insurance, Access, and the Healthcare Navigation Problem
The gap between what the evidence supports and what patients actually receive is nowhere more visible than in oral appliance therapy. A 2022 analysis of Medicare claims data found that fewer than 12 percent of Medicare-enrolled OSA patients received any form of oral appliance therapy, despite the evidence supporting its use and Medicare’s established coverage policy.
The path of least clinical resistance — CPAP prescription — dominates because it requires the fewest steps, and because most primary care physicians aren’t familiar enough with dental sleep medicine to discuss it as an equivalent option.
Navigating insurance coverage requires knowing several things. A physician diagnosis of OSA based on a qualifying sleep study is required for coverage under virtually all major plans — a dentist can’t initiate coverage without physician involvement. Most plans require documentation of OSA severity sufficient to meet coverage thresholds, and in many cases prior CPAP trial documentation showing intolerance.
Some plans will cover OAT as first-line therapy without a CPAP trial if the prescribing physician explicitly documents a medical reason why CPAP is inappropriate for that patient. The appeals process, when initial claims are denied, has a meaningful success rate — particularly when supported by a letter from the treating sleep physician explaining the clinical rationale.
The access problem extends beyond insurance. Dental sleep medicine is concentrated in urban and suburban areas, with significant deserts in rural regions. Patients in rural areas often have no access to Diplomate-credentialed providers within a reasonable driving distance. Telehealth dental sleep medicine — using digital impressions taken by a local general dentist and remotely supervised titration — has partially addressed this gap, but managing side effects remotely requires both patient education and readily available escalation pathways when problems arise.
The field hasn’t fully solved the rural access problem. Worth saying that plainly, as part of honest patient communication.
Common Questions About Oral Appliances Actually
Can I use an oral appliance if I have severe sleep apnea?
Yes, with important caveats. The AASM guidelines support oral appliance use in severe OSA (AHI above 30) for patients who prefer it or cannot tolerate CPAP. AHI normalization rates are lower in severe disease than in mild-to-moderate cases, and objective follow-up testing to confirm adequate control is mandatory — not optional. Some patients with severe OSA achieve excellent control with well-fitted oral appliances; others don’t, and those patients need to be redirected to CPAP, combination therapy, or surgical evaluation.
The decision must involve a sleep physician, not a dentist operating independently.
Will my insurance cover an oral appliance?
Most major commercial insurers and Medicare cover custom oral appliances for diagnosed OSA, but coverage criteria vary significantly by plan. Requirements typically include physician diagnosis from a qualifying sleep study, documentation of OSA severity, and in many cases prior CPAP trial documentation. The dental office providing the appliance typically handles insurance billing; ask for a detailed written breakdown of expected out-of-pocket costs before committing to treatment.
Medicare patients should verify that the provider is enrolled as a Medicare DME supplier, which is a different enrollment process than standard Medicare provider status.
How long does the titration process take, and when will I feel better?
Most patients notice subjective improvement in snoring and morning energy within the first two to four weeks, even before reaching optimal protrusion. The full titration process to reach the minimum effective protrusion takes six to twelve weeks of gradual advancement. Objective confirmation with a follow-up sleep study should happen after titration is complete — typically three to four months after the initial fitting.
Side effects like jaw soreness are most prominent in the first month and usually diminish significantly by weeks six to eight as muscles adapt.
What happens to my bite with long-term oral appliance use?
Bite changes are common and occur in the majority of long-term users. Most changes are minor reductions in overbite and overjet and aren’t symptomatic. Clinically significant changes occur in approximately 14 percent of long-term users based on the best available longitudinal data. Morning repositioning exercises reduce but don’t eliminate this risk.
Your bite should be assessed at every annual follow-up visit, and your provider should photograph your occlusion at baseline so any changes can be quantified rather than estimated.
Is there a test to predict whether an oral appliance will work for me before I invest in one?
No single test reliably predicts response, but several approaches improve the probability of matching the right patients to oral appliance therapy. Drug-induced sleep endoscopy (DISE) — a procedure in which sedation is used to reproduce sleep-related airway collapse while an endoscope visualizes the site and pattern — provides the most direct anatomical information. Patients whose collapse is primarily at the tongue base or lateral walls, and not complete concentric collapse at the palate, respond better to mandibular advancement.
A daytime mandibular advancement test (DMAT), performed in the clinic with temporary protrusion to assess snoring reduction, provides a lower-cost directional signal. Predictive models incorporating BMI, jaw anatomy, AHI, and neck circumference have been developed and validated but aren’t yet widely used in routine practice.
The machine that sits on your nightstand unused is treating nobody. The appliance you actually wear every night, even if it doesn’t achieve perfect AHI normalization, is doing real work. The best sleep apnea therapy is the one that happens — consistently, every night, for years.
Marcus’s story ends well. His oral appliance took eight weeks to titrate properly. His follow-up sleep study showed an AHI of 6 — not zero, but well within the treated range. His wife told him within the first week that she could no longer hear him breathing from her side of the bed. He doesn’t think about the appliance much anymore. He puts it in, falls asleep, wakes up feeling like a person again.
The best medical devices are the ones you forget you’re wearing.
References
Editorial StandardsCorrectionsMedical DisclaimerAbout Our ContentAffiliate DisclosureSite Map